Clinical image
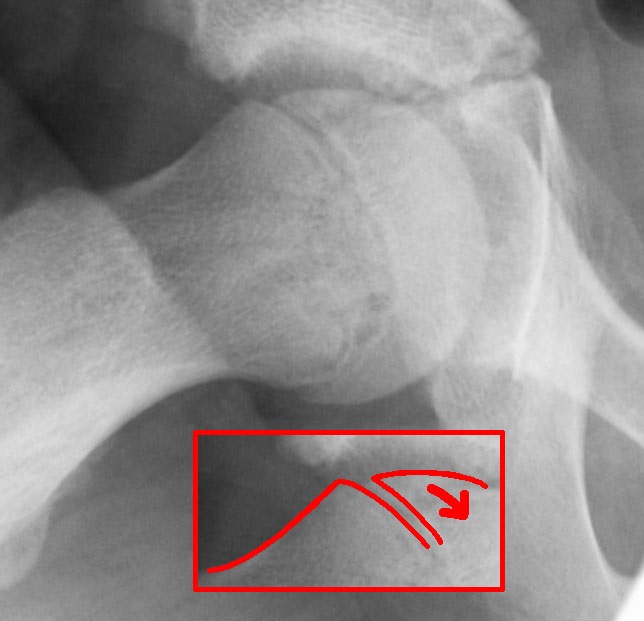
Radiograph showing slipped capital femoral epiphysis. Source: Wikimedia Commons — Dr. Jochen Lengerke; CC0 1.0. Image binary is embedded locally in this package; original source and licence are retained.

Define
- Disorder of proximal femoral metaphysis
- That leads to slippage of the metaphysis anteriorly and superiorly
- relative to epiphysis, which remain anatomically positioned
M/C
- Boys
- Increased weight
- Hormonal conditions
- Hypopitutary
- Hypothy
- Hypogonadism
- Rickets
C/F
- Overweight boy
- Thigh/knee pain
- Limping
- minor trauma
- 11-14 y
C/E
- Short and ER
- FADER position
- F, abd, IR restricted
- Additional ER if hip is flexed further
Inv
- X ray
- Klein line
- Decreased ep height
- Widening of physis
- Remodeling changes , sclerosis
Klein line
Classification
Functional
- Stable
- Unstable
Lodder, 55 slips in 54 children, multi centre
- avn 47% in unstable hip
Cronological
a/c
- <3 weeks
- abrupt
c/c
3weeks
- gradual
a/c on c/c
3weeks symptoms
- sudden increase in pain
Grading
- Southwick
- Laterl view
- diff b/w two sides
- Grade 1: <30 degree
- 2: 30-50
- 3: >50
Treatment
- Aim
- prevent any progression without complication
- Stable or chronic: PIS
- Unstable and acute:
- PIS difficult
- Risk of AVN
- OR
- Fish sub capital
- Dunn trochanteric
- Ganz
Uglow and clark
Key points
| Slip Grade | Timing | Stability | Treatment |
|---|---|---|---|
| 1 and 2 | Any | Stable | PIS |
| 1 and 2 | < 24 hours | Unstable | Reposition and Pin |
| 1 and 2 | >24 hours | Unstable | PIS |
| 3 | <24 | Unstable | Reposition and Pin |
| 3 | >24 | Unstable | PIS (Delay for 3 weeks); give traction to avoid AVN |
PIS
More anterior entry
6.5 mm fully threaded reverse cutting screws
Use fluoroscopy to avoid blind spot
No more than 3-5 threads, 5mm below subchondral
PWB to FWB
Timing
- Stable: ASA safly possible
- Unstable
- Lownders et al:
- AVN decreases if done with in 24 hours
- Peterson
- Less AVN 24 hours
- Loder
- Less AVN with in 48 hours
- Lownders et al:
Contralateral
- Symptomatic: fix
- Asymptomatic: fix if
- < 10 y
- endocrine
- poor compliance
- nature of current slip
Compli
- AVN
- Chondrolysis: rapid and progressive loss of cartilage
- Deformity
- OA
- LLD