Jersey finger
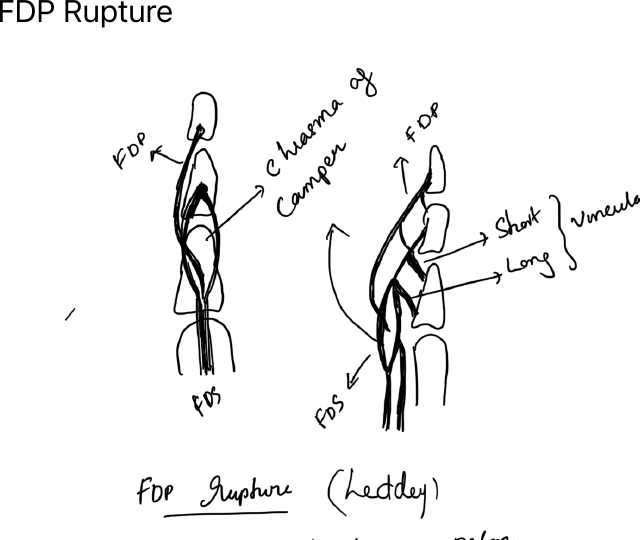
Avulsion of the flexor digitorum profundus (FDP) tendon from the distal phalanx is commonly called jersey finger. The ring finger is most often involved.
The usual mechanism is forced extension of an actively flexed distal interphalangeal joint.
Clinical features
- pain and tenderness over the volar distal finger
- inability to actively flex the DIP joint
- the retracted tendon may be palpable proximally
Test FDP by holding the PIP joint extended and asking the patient to flex the DIP joint.
Leddy and Packer classification
Type I
- Tendon retracts into the palm
- Vincular blood supply is disrupted
- Requires early repair
Type II
- Tendon retracts to approximately the PIP level
- Long vinculum remains intact
Type III
- Large bony fragment catches at the A4 pulley, limiting retraction
Type IV
- Bony avulsion occurs and the tendon separates from the avulsed fragment and retracts proximally
Imaging
Plain radiographs assess for a bony avulsion. Ultrasound or MRI can help identify the tendon level when the diagnosis or retraction level is uncertain.
Treatment
Acute complete avulsions are generally treated surgically by tendon reattachment. Timing is particularly important in Type I injuries because the tendon is retracted and its vascular supply is compromised.